Introduction
Arteriovenous malformations (AVMs) are high-flow developmental vascular anomalies in which the feeding arteries are directly connected to a venous drainage network without an interposed capillary bed. The distinguishing feature of an AVM is that shunting occurs through a collection of tortuous dysmorphic vessels, referred to as a nidus [1-3]. AVMs can occur anywhere in the body; however, brain AVMs (BAVMs) are of special concern as they can cause neurological dysfunction.
BAVMs have a population incidence of 1.12-1.42 cases per 100,000 person-years [4]; no sex difference has been identified so far [5]. The most common presentation is intracranial hemorrhage (ICH), and BAVMs are the second most common cause of ICH after cerebral aneurysms [1]. The annual risk of bleeding from BAVM reaches approximately 2% to 4%, depending on whether the BAVM is ruptured or not [6]. Reported risk factors associated with hemorrhage occurrence include deep and infratentorial location, exclusive deep and single venous drainage, nidus size less than 3 cm, and the presence of an associated aneurysm [7].
BAVMs are typically first identified in cross-sectional imaging – computed tomography (CT) or magnetic resonance imaging (MRI) [1]. However, these modalities do not provide as detailed imaging of the nidus architecture as digital subtraction angiography (DSA), which remains the reference standard for the diagnosis and treatment planning of BAVM [1,2,8].
The objective of this study was to determine whether there is a correlation between characteristics of BAVM and coexistence of intracranial aneurysms (IAs). The current analysis considers the radiographic features of BAVMs and aneurysms, as well as clinical presentation with ICH.
Material and methods
Patient selection
A total of 89 patients with BAVMs, detected via cerebral DSA between 2011 and 2022, were enrolled in this study. The material was analyzed retrospectively to collect the following data: demographic features, size and location of the BAVM nidus, source of arterial supply and characteristics of venous drainage of the BAVM, presence of IAs, as well as the presence of ICH. The CT imaging was used to determine whether the patient had experienced ICH. All patients included in the study had undergone DSA with 2D and rotational 3D DSA technique. Patients who had previously undergone therapeutic interventions of their BAVMs were not included in the study.
BAVM characteristics
In this analysis, initial BAVM presentation was defined as hemorrhagic or nonhemorrhagic, according to radiological imaging. The lesions were assessed according to the Spetzler-Martin Grading System [9], using the Supplementary Grading [10] and the Combined Spetzler-Martin grade [10]. BAVM size was recorded from cerebral angiography and defined as the largest diameter of the nidus. The largest diameter was measured in anteroposterior, lateral, and oblique projections. According to size, BAVMs were classified into three size categories: small (< 3 cm), medium (3-6 cm), and large (> 6 cm). Patterns of venous drainage were determined from the angiogram and defined as deep or superficial, whereas BAVM location was classified as supratentorial and infratentorial.
Aneurysm characteristics
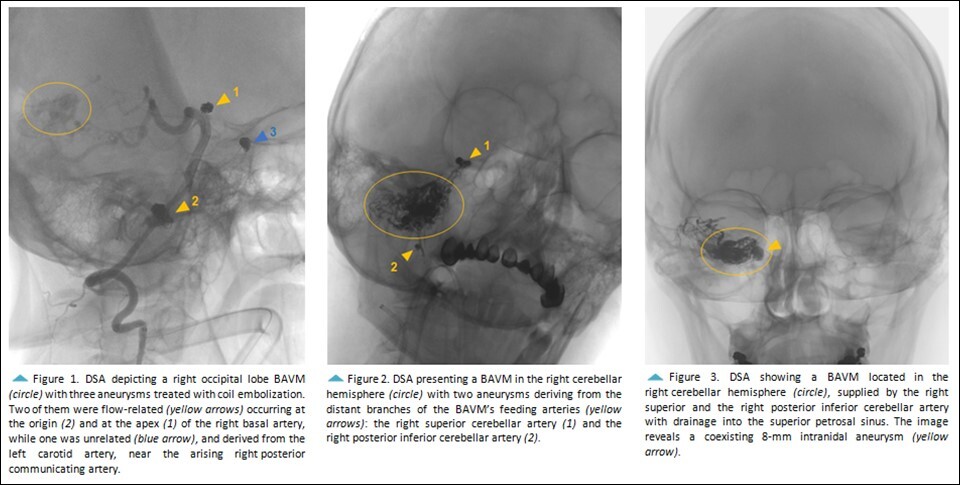
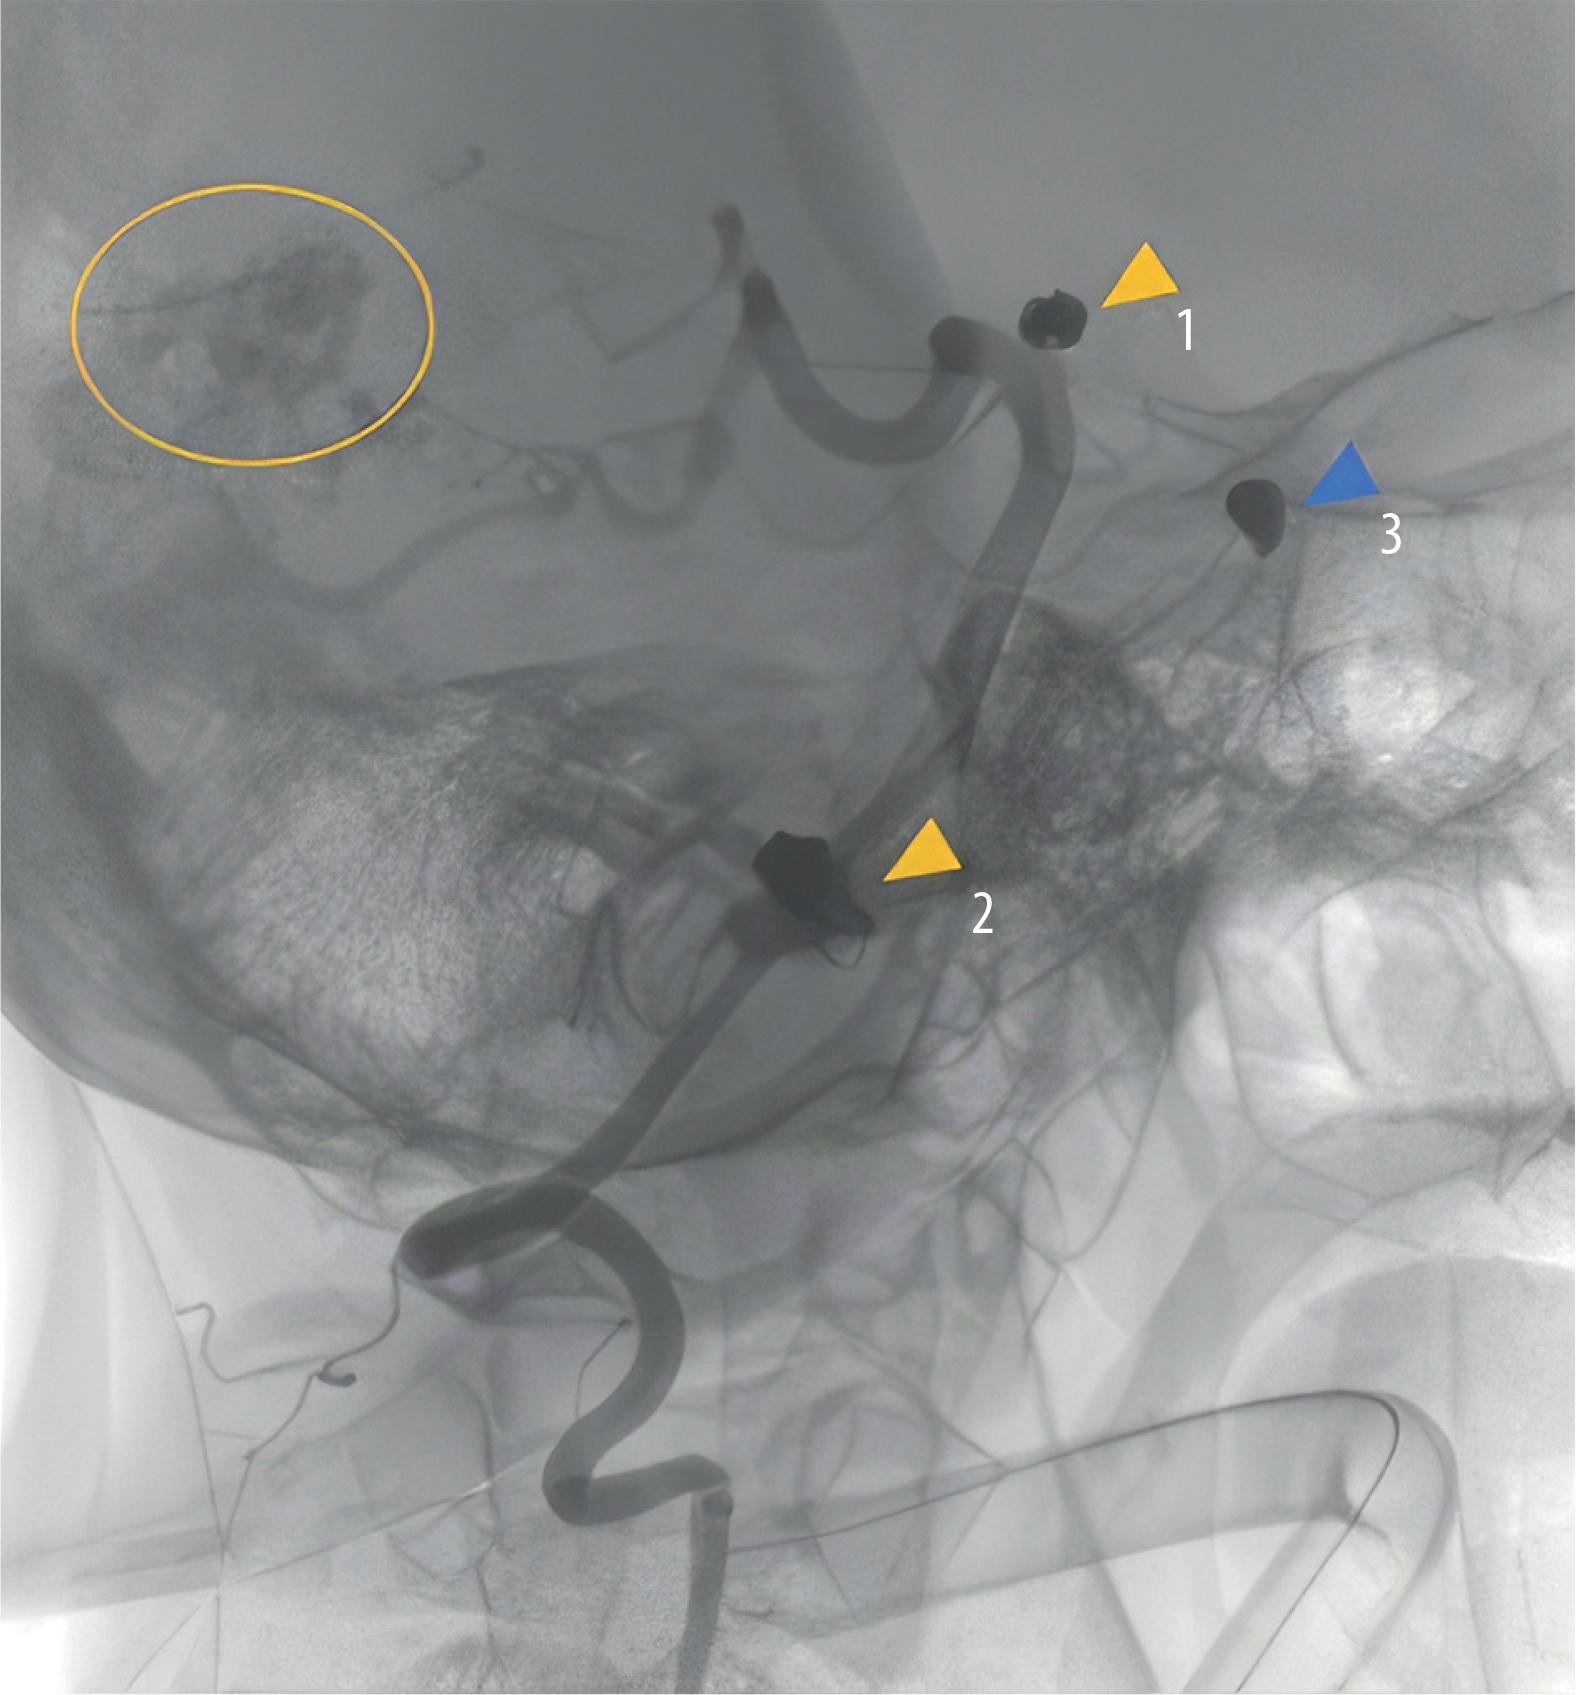
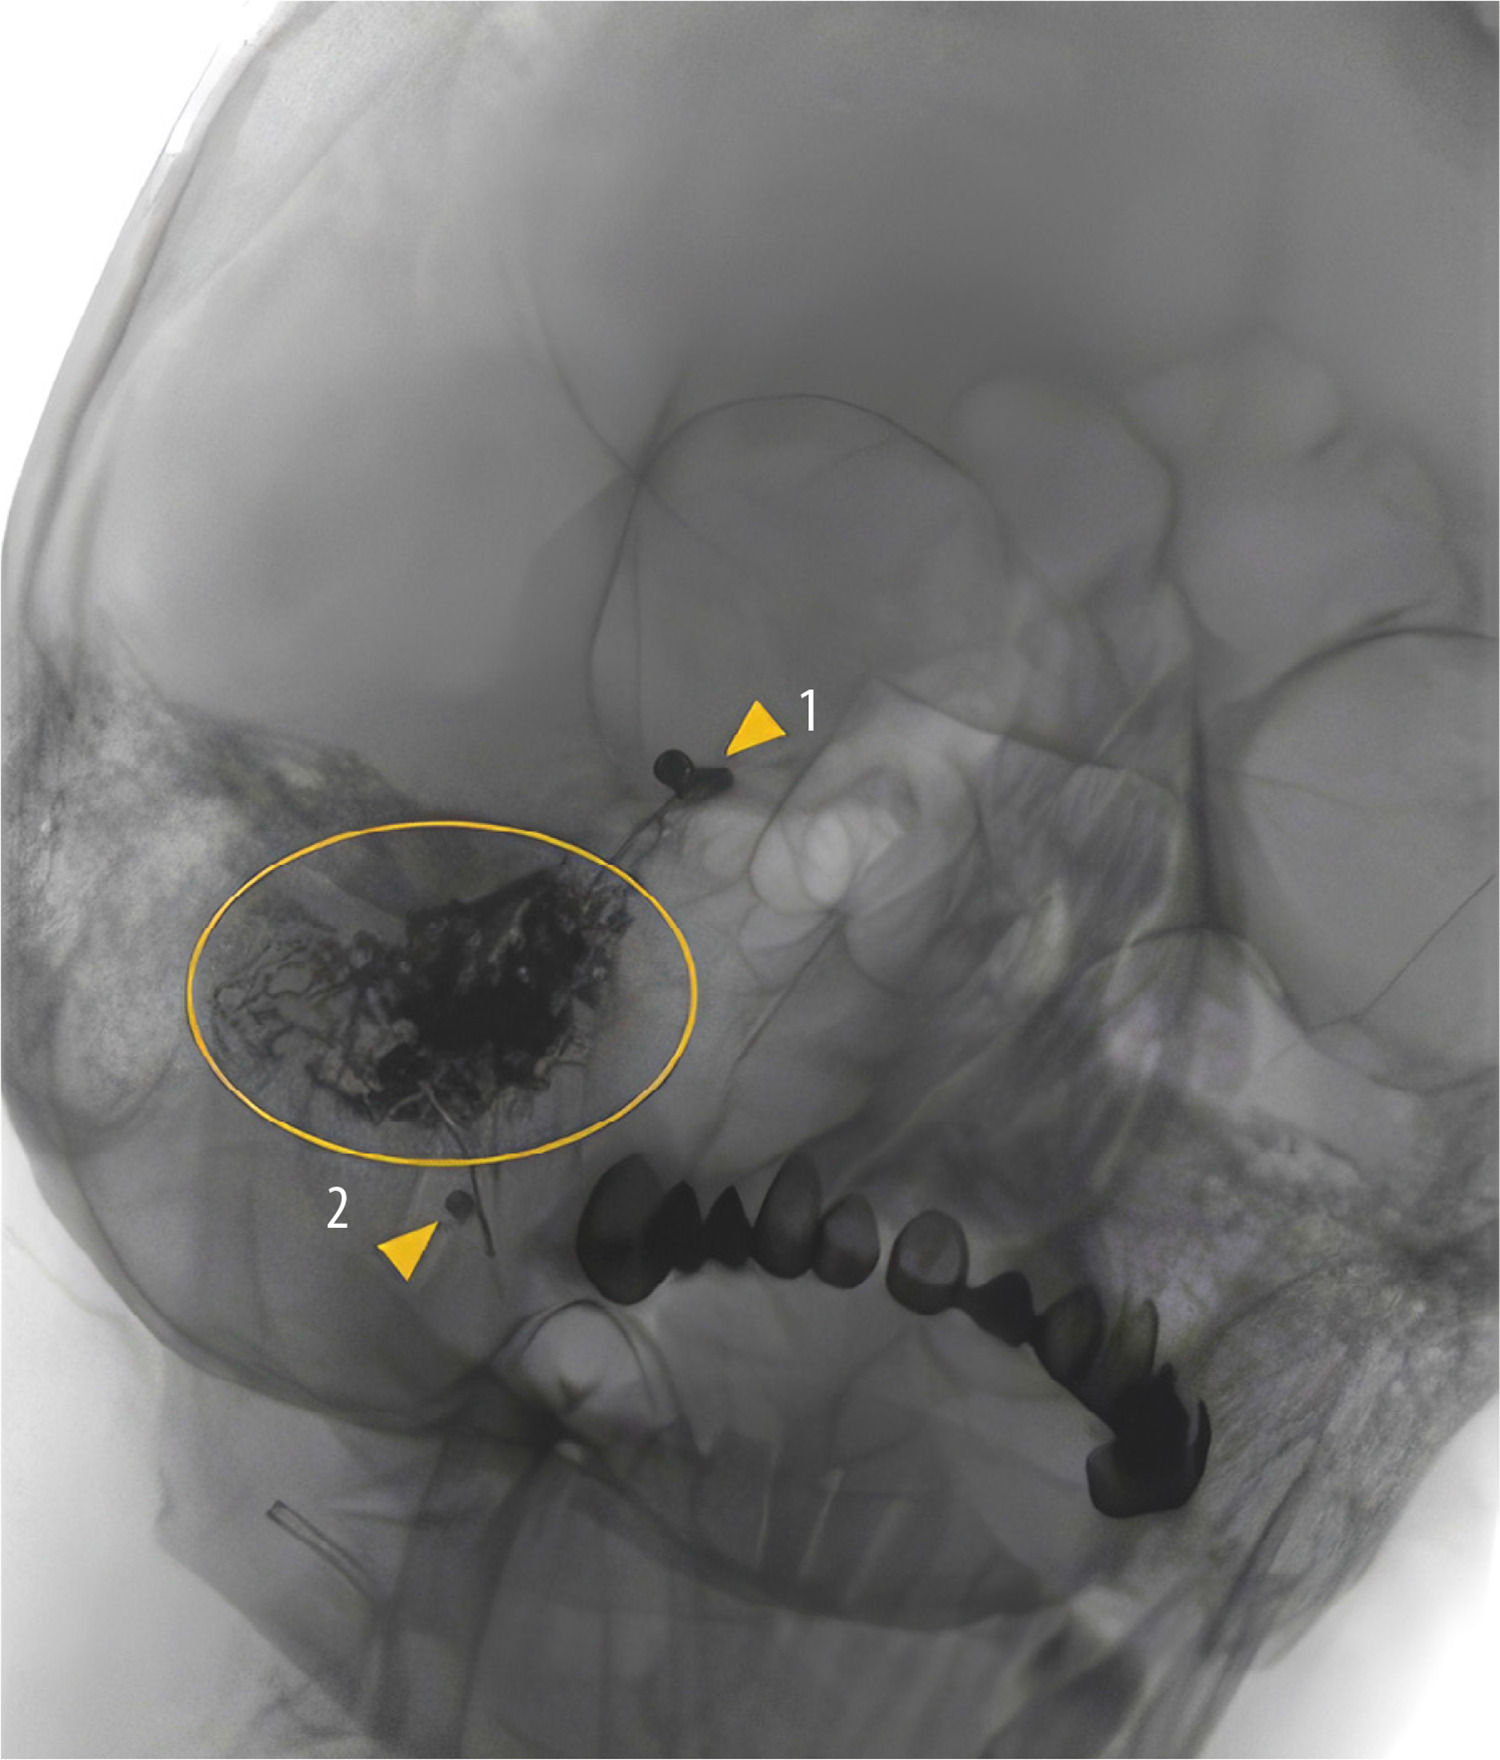
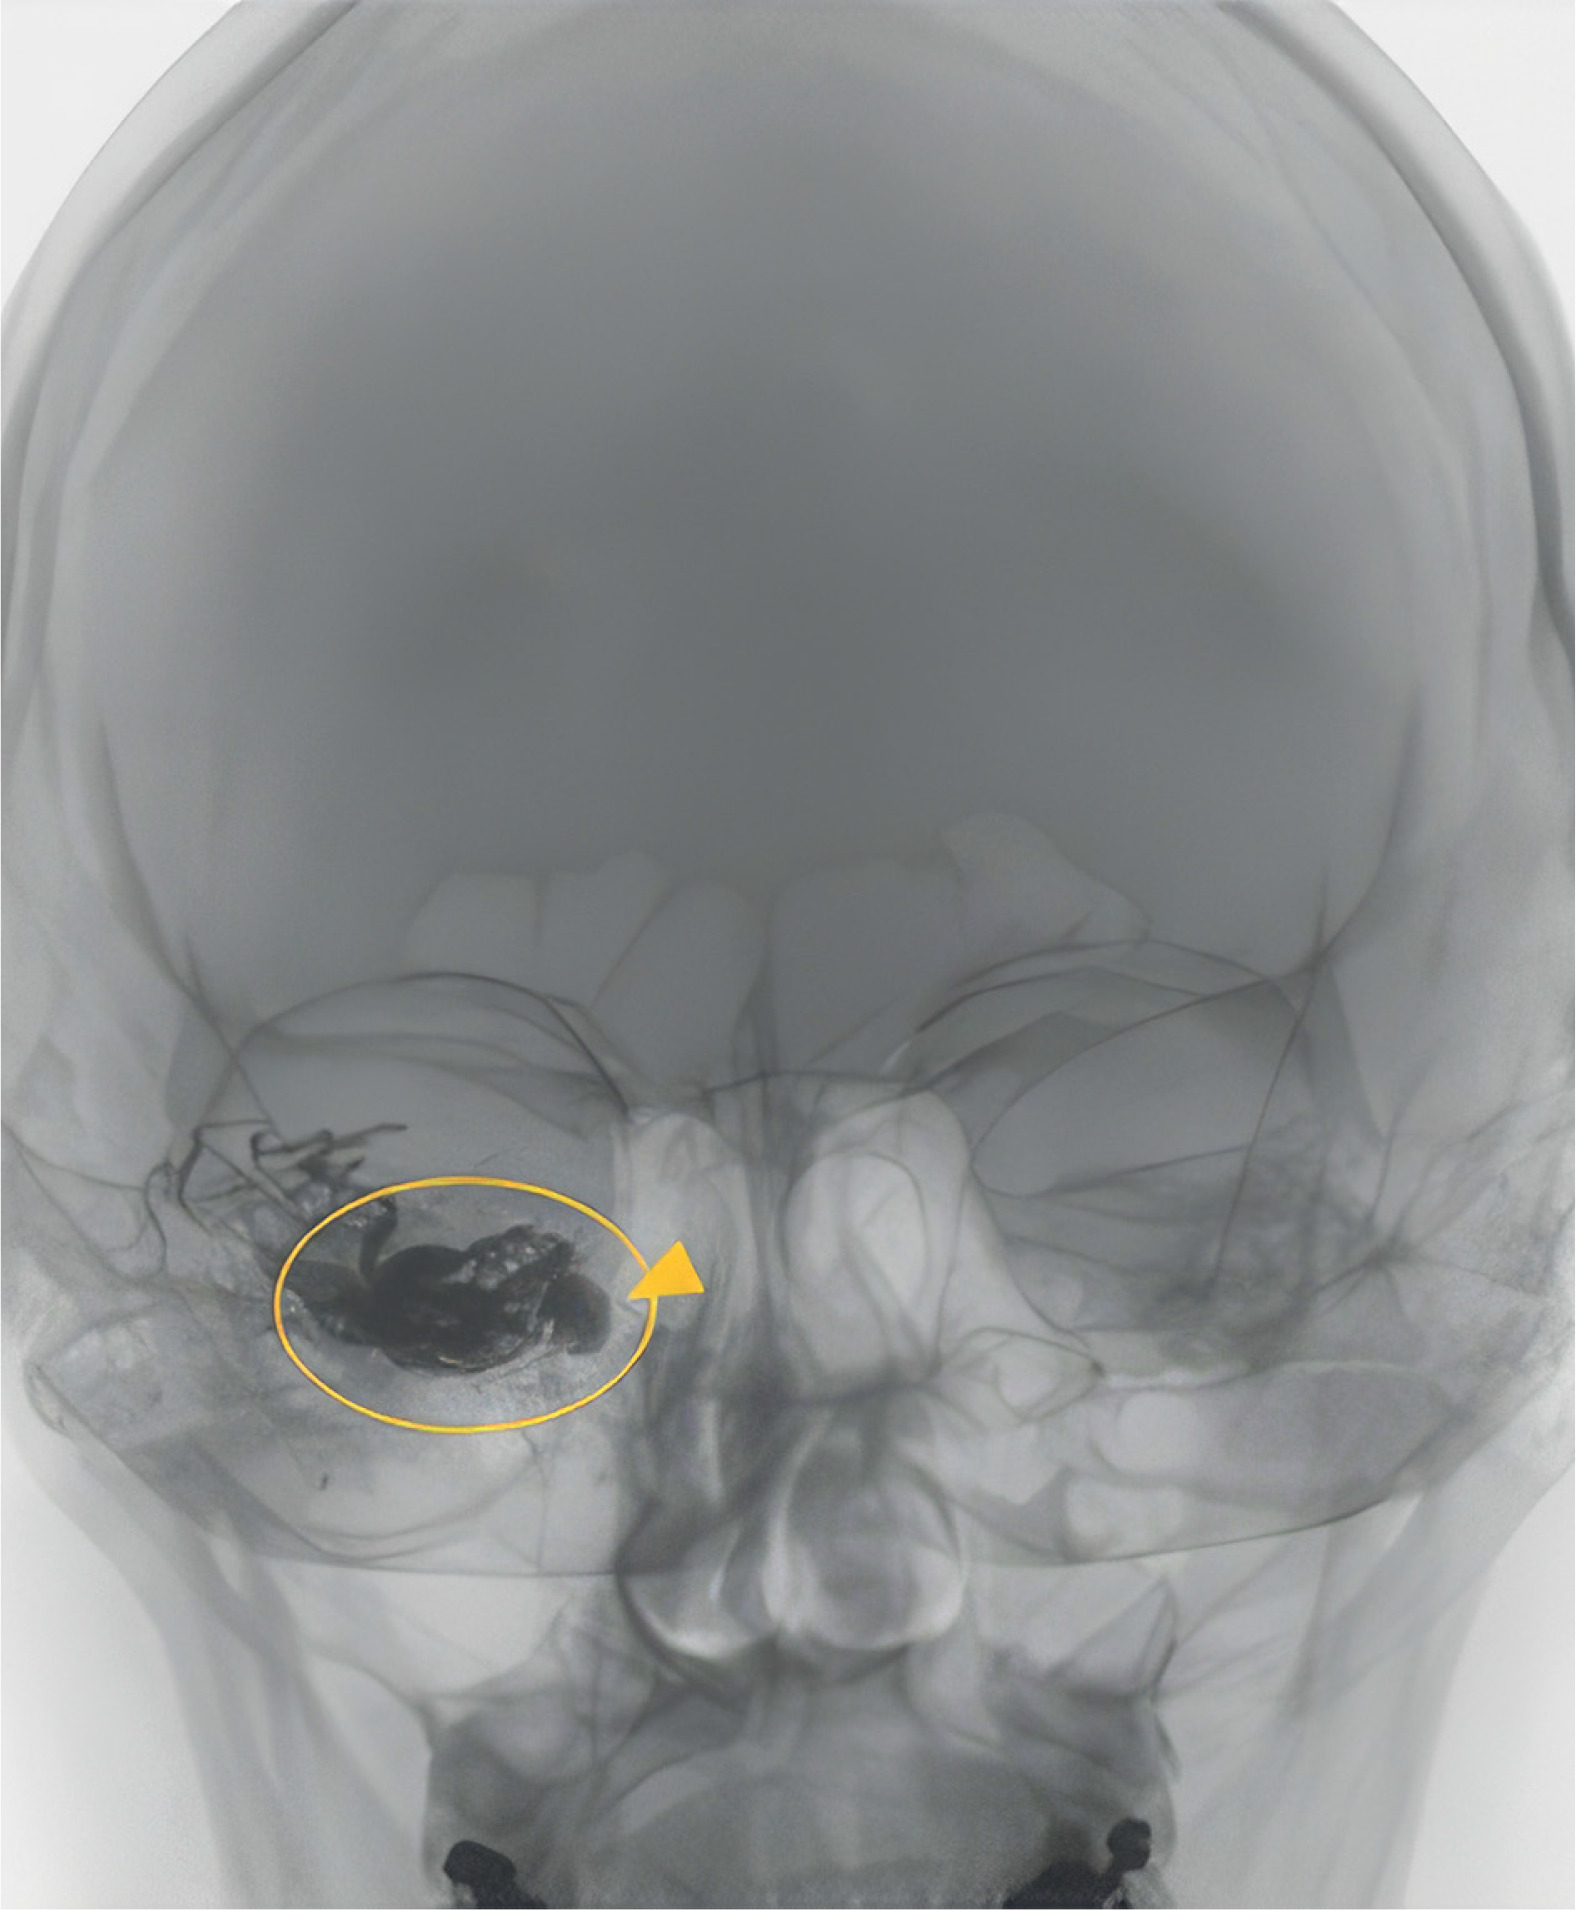
There is no unanimously accepted classification of coexisting intracranial aneurysms; therefore, considering the assumptions of this study, the aneurysms were allocated to the following subgroups: intranidal, flow-related, and aneurysms unrelated to the shunt flow to the BAVM. Such differentiation is a simplified version of a widely adopted model proposed by Redekop [11]. Aneurysms were coded as unrelated if they were located on vessels that were not BAVM feeders (Figure 1). Flow-related aneurysms arise along the course of arteries implicated in the perfusion of the nidus and, as a result, are hemodynamically related to the BAVM (Figures 1 and 2). Finally, intranidal aneurysms occur within the boundaries of the nidus (Figure 3) [5]. Other recorded features of aneurysms were their size and multiplicity.
Figure 1
DSA depicting a right occipital lobe BAVM (circle) with three aneurysms treated with coil embolization. Two of them were flow-related (yellow arrows) occurring at the origin (2) and at the apex (1) of the right basal artery, while one was unrelated (blue arrow), and derived from the left carotid artery, near the arising right posterior communicating artery
Statistical analysis
All data were analyzed using Statistica 12 (StatSoft). Qualitative statistics included χ2 tests for comparison between BAVM localization, BAVM type, BAVM size measured in size intervals, arterial supply, venous outflow, density, eloquence, bleeding and aneurysm types, coexistence and multiplicity. To evaluate correlations between quantitative data (SM grades, BAVM size), aneurysms (coexistence and number) and bleeding, t-tests and Mann-Whitney U tests were performed. A Shapiro-Wilk test was performed to estimate whether the distribution of the data followed a nominal distribution. The BAVM size and aneurysm type were examined using one-way ANOVA with post-hoc Bonferroni correction if ANOVA results were statistically significant. Two-way ANOVA was used to evaluate the combination effect of coexistence and number of aneurysms on BAVM size. Statistical significance for each analysis was defined as p < 0.05.
Results
Population analysis
A total of 89 patients with angiographically verified BAVMs were available for this study. The population included 45 males (50.56%) and 44 females (49.44%). The mean age of BAVM diagnosis was 41.81 ± 17.73 years (age range 12-79 years). A total of 89 BAVMs were discovered. None of the BAVMs was multiple. Demographic data are summarized in Table 1.
Table 1
Demographic and morphological characteristics of 89 patients with BAVMs
Analysis of BAVMs
In 51 (57.30%) BAVMs, the source of arterial supply was single, and in 38 (42.70%) it was multiple: double in 28 (31.46%) and triple in 10 (11.24%) cases. BAVMs feeding arteries most often originated from the middle cerebral artery (MCA; 40.88% of a total of 137 arterial sources identified in the whole BAVM population), less frequently from the posterior cerebral artery (PCA; 25.55%), the anterior cerebral artery (ACA; 16.79%) and other arteries: cerebellar arteries (8.76%), internal carotid artery (ICA; 7.30%), and external carotid artery (ECA; 0.73%). The origin of BAVMs feeding arteries is depicted in Table 2.
Table 2
Origin of the BAVM feeding vessels
No significant predilection of left-sided lesions compared to right-sided lesions (49 vs. 40) was observed. The average maximum diameter of the nidus was 26.48 mm ± 13.19 mm (range 6-63 mm). Of the 89 BAVMs, 52 (58.43%) were < 3.0 cm, 36 (40.45%) were between 3 and 6 cm, and 1 (1.12%) was > 6 cm. Infratentorial location was less represented compared to supratentorial and accounted for 11 BAVMs (12.36%).
Thirty-one (34.83%) BAVMs were located in eloquent regions of the brain, whereas BAVM morphology was defined as compact in 54 (60.67%) lesions. Thirty-seven (41.57% of all BAVMs) presented with ICH. Venous drainage pattern was superficial in 59 (66.29%) and deep in 30 (33.71%) cases. Of the 89 BAVMs discovered, 33 (37.08%) were Spetzler-Martin (SM) grade 1, 24 (26.97%) were grade 2, 21 (23.60%) were grade 3, 11 (12.36%) were grade 4. None of the BAVM presented an SM grade higher than 4. BAVM characteristics according to Spetzler-Martin grade, supplemental grade, and combined grade, are presented in Table 3.
Table 3
BAVM distribution by Spetzler-Martin grade, supplemental grade, and combined grade
Analysis of intracranial aneurysms
Within the entire BAVM patient population, 28 patients (31.46%) were found to have one or more IAs. There were 16 (57.14%) females and 12 (42.86%) males in this group, ranging in age from 12 to 79 years (mean age, 43.71 ± 19.79 years). A total of 42 associated aneurysms were detected in the study. Sixteen (57.14%) of 28 patients had single aneurysms, and 12 (42.86%) had multiple aneurysms. Of 42 IAs, 26 flow-related aneurysms were detected in 16 patients (57.14% of all patients with aneurysms), 10 intranidal aneurysms in 11 patients (39.29%), and 6 unrelated aneurysms were found in 6 patients (21.43%). Among the 28 patients with IAs, 11 patients (39.29%) presented exclusively flow-related aneurysms, 11 (39.29%) had exclusively intranidal aneurysms, and in 1 patient (3.57%) an unrelated type of aneurysm was the only one existing. Five patients (17.86% of all patients with aneurysms) had more than one type of aneurysm – all of these patients had flow-related and unrelated aneurysms at the same time. Intracranial hemorrhage was observed in 16 (57.14%) patients with coexisting IAs: 9 patients with flow-related aneurysms, 6 with intranidal aneurysms and 3 with unrelated aneurysms. The features of BAVM patients with coexisting IAs are listed in Table 4.
Table 4
Characteristics of intracranial aneurysms associated with BAVMs
Comparison of aneurysm vs. non-aneurysm BAVM patients
Cerebellar location of BAVMs, as well as cerebellar source of BAVM arterial supply, was more frequent in BAVM patients with associated aneurysms (p = 0.02, p = 0.04). There was also a statistically significant relationship between multiple sources of arterial supply and a non-hemorrhagic presentation of BAVMs (p = 0.04). Furthermore, BAVMs were found to be larger when the source of arterial supply was multiple (p < 0.05). This finding persisted when the analysis was restricted to small (< 3 cm) (p < 0.05) and medium-sized (3-6 cm) (p < 0.05) BAVM groups. Conversely, the interaction could not be confirmed in the large BAVMs (> 6 cm), as the group consisted of a single malformation. BAVM size, however, was not found to be influenced by the co-existence of IAs, including multiple aneurysms, regardless of whether BAVMs were considered together, or in separate groups, according to their size category. A multivariate logistic model including the number of sources of arterial supply and the coexistence of aneurysms, did not reveal any statistically significant correlation (p = 0.57). The venous drainage pattern was not significantly associated with the presence of IAs (p = 0.75). No correlation was found for either nidal diffuseness or for eloquent location (p = 0.35, p = 0.55). As regards Spetzler-Martin grading, patients with IAs did not significantly differ from patients without aneurysms (p = 0.98 for SMG, p = 0.62 for SM total score). Hemorrhagic presentation did not show an association with BAVM size (p = 0.30) and with its cerebral location (p = 0.78). In contrast, the coexistence of IAs was found to be significantly associated with BAVMs presenting with hemorrhage (p = 0.04). In terms of type and number of co-occurring aneurysms, no significant difference was identified when analyzing the bleeding rate (p = 0.42, p = 0.38). The relationship between BAVM features and the co-occurrence of IAs is presented in Table 5.
Table 5
Characteristics of BAVM patients with and without associated aneurysms
Discussion
BAVM in the literature
BAVMs were thought to be solely congenital lesions; however, there has emerged a theory of a two-hit mechanism. It states that apart from genetic predisposition or already present vascular abnormality, there is a need for a vascular injury to occur in order for BAVMs to develop [2,5].
Only 12% of BAVMs become symptomatic, usually around the third or fourth decade of life [6], although in 45% of cases the presentation is an ICH [12]. Ruptured BAVMs account for 2% of all hemorrhagic strokes [13-15], and at the same time are the leading cause of non-traumatic intracerebral hemorrhage in individuals less than 35 years old [6]. Other mechanisms of neurological dysfunction in BAVM patients are mass effect, which increases the risk of seizures, and the “steal phenomenon”. The latter contributes to non-nutritive blood flow in the brain parenchyma adjacent to the BAVM, leading to slowly progressive neurological deficits [1].
The prevalence of BAVM-associated aneurysms ranges considerably between studies (2.7-58%), although the most commonly cited is from the 10-20% range, with a recently reported rate of 18% [7,9]. There are several theories explaining the development of IAs coexisting with BAVM. Both lesions may be considered either as congenital malformations or co-occurring accidentally. Multiple studies highlight the flow-related hypothesis suggesting that the aneurysm occurs secondary to hemodynamic stress related to the BAVM increased flow. This theory is supported by a documented regression of prenidal aneurysms after BAVM obliteration as well as the fact that most aneurysms occur within the arteries proximal to the BAVM [3-5].
The key goal of BAVM management is to preserve neurological function, mainly by preventing hemorrhagic events and their consequences [4]. Contemporary treatment options for BAVM include observation with medical management, microsurgical resection, endovascular embolization and stereotactic radiotherapy [3]. Studies dealing with the endovascular treatment of BAVM-associated IAs are substantially heterogeneous regarding treatment method and rationale for treatment [16]. Management priorities are dictated by clinical presentation, with determination of the source of hemorrhage if present, and the relationship of the aneurysm to the BAVM nidus [5].
The present study is a comparative analysis of BAVM characteristics in BAVM patients with and without coexisting IAs. Angioarchitectural features comprised BAVM size, location, source of arterial supply, and venous drainage pattern, including determination of Spetzler-Martin grade, whereas clinical presentation was divided into hemorrhagic and nonhemorrhagic. A simplified Redekop et al. [11] model was used to allocate IAs into three subgroups, depending on their relationship to the flow of blood through the BAVM.
BAVM features
In line with the literature, no predilection regarding a patient’s sex was observed in this study [17]. The origin of the BAVM feeders was in most cases the MCA, as reported by Milatović et al. [14]. Despite available data suggesting that small BAVMs present a higher rate of hemorrhage [4], it was not supported by our analysis. Long-term studies identify small BAVM size as a risk factor for hemorrhage at initial presentation, while BAVMs larger in size seem to be more predictive for increased risk of future hemorrhagic events [4].
Interestingly, in our study, BAVM size appeared to be positively correlated with the number of sources of the BAVM arterial supply. In the meta-analysis by Ai et al. [18], a single BAVM feeder was identified as a predictor of hemorrhagic presentation compared to multiple feeders. Nonetheless, the examined population was pediatric, and only 2 studies investigated a single feeder as a potential risk factor for hemorrhage. Such a relation was confirmed by Lv et al. [17] in a retrospective study of 302 BAVM adults. In this perspective, the positive correlation between the size and the number of feeders described in our study appears to indirectly support the aforementioned relationship with hemorrhage.
Coexistence of aneurysms
The coincidence of BAVMs and IAs reached 31.46% in this study, which is somewhat above the frequently reported rate of about 20% [6,19-21]. Among BAVM-associated IAs, flow-related type was predominant, representing 61.90% of all aneurysms, compared to 71.40% in a large Cagnazzo et al. [20] review. The same study has shown that flow-related aneurysms were the most common source of aneurysmal hemorrhage, accounting for nearly 80% of cases [20]. The hemorrhage rate of BAVMs with associated IAs was 57.14% in our analysis and proved to be significantly higher than in the BAVM group without IAs, which confirms that BAVM-associated IAs increase the risk of an intracranial hemorrhage. However, when stratified by their hemodynamic relationship to the BAVM, the aneurysms had no influence on hemorrhagic events. Similarly, multiple aneurysms appeared not to affect the bleeding rate in this analysis, and such an association remains unclear according to natural history studies [17].
Hemorrhagic presentation
The hemorrhage rate in the studied BAVM population reached 41.57%, which is close to the lower limit of the reported prevalence of 41 to 79% [1]. Different risk factors for BAVM hemorrhage have been explored so far, yet only a few of them are reported consistently across available literature [22]. A recent large meta-analysis identified high-risk factors as the presence of an associated aneurysm, deep location, infratentorial location, exclusive deep venous drainage, single venous drainage, and nidus size less than 3 cm [7]. In the current study, BAVM size, deep venous drainage and aneurysm type did not influence the risk of hemorrhagic events. Likewise, SM grade appeared not to be associated with risk of BAVM bleeding. On the other hand, BAVM patients with multiple sources of arterial supply were less prone to bleeding.
According to the systematic review by Goldberg et al. [22], prior hemorrhage and deep BAVM location are the most often mentioned risk factors for future hemorrhage in patients diagnosed with BAVM. In our study, infratentorial BAVMs tended to have a higher incidence rate of IAs, which is consistent with the review by Lv et al. [21]. This relationship was further supported in our analysis by an analogical observation regarding BAVMs with a cerebellar source of arterial supply, which also showed a greater occurrence of IAs. Unfortunately, the insufficient number of BAVMs in these subgroups did not allow us to draw conclusions regarding a definite relationship. In a large prospective study by Khaw et al. [23], posterior fossa BAVM location was identified as an independent risk factor for hemorrhage as the initial presentation. This relationship could be explained by an increased blood flow demand present in the cerebellum and thalamus [16], although such an observation was not confirmed by our study results. Besides associated aneurysms, the concentration of eloquent neurological structures within the limited space of the infratentorial compartment makes the management of BAVMs particularly challenging and may result in poor final outcomes [24].
Limitations
The limitations of this study are primarily due to its retrospective single-center nature including inherent sampling bias. Because of a relatively small number of particular BAVM and aneurysms subgroups, we were not able to assess the impact of some of the examined features. In addition, our analysis was limited in terms of differentiation as to whether hemorrhages were due to IAs or the BAVM itself, which is important as an aneurysm per se is considered an independent risk factor for rupture [7]. Furthermore, the model used to classify aneurysms was a simplified version of that proposed by Redekop et al. [11], lacking distinction between proximal and distal subtypes of flow-related aneurysms.
Conclusions
In this retrospective study, the coexistence of brain arteriovenous malformation and intracranial aneurysms was observed in 31.46% of patients. Patients with both BAVMs and IA have significantly higher rates of hemorrhagic presentation than those without aneurysms. Multiple sources of BAVM arterial supply are significantly associated with a lower risk of ICH. Other examined factors, such as BAVM location, morphology of the nidus, pattern of venous drainage, SM grade and aneurysm type were not identified as predictors of hemorrhage in this analysis. IAs tended to be more frequently associated with infratentorial BAVMs. The extent of BAVM arterial supply showed a significant positive correlation with BAVM size for malformations smaller than 6 cm.

